

Table of Contents
Here is your Rural Health Transformation Program readiness checklist. The Rural Health Transformation Program is a once-in-a-generation opportunity to reshape rural care. But the money alone won’t create impact, your readiness will.
Have you asked yourself, “How prepared are we to transform our health center when the funds arrive?”
The RHTP is a five-year, $50 billion federal investment designed to help states transform rural health care delivery, improving access, quality, and outcomes through innovation, workforce, and technology. All 50 states received RHTP awards from CMS in December 2025, with funding running from 2026 to 2030.
That means your state is issuing RHTP-funded RFPs and subawards now.
This post is not a breakdown of every line in the statute. It’s a Rural Health Transformation Program readiness checklist for CEOs, CMOs, CDOs, and operational leaders who don’t just want to “chase a pot of money,” but actually use those dollars to transform care.
Use these questions with your leadership team. If too many answers are “I’m not sure” or “we haven’t really talked about that,” you’re not ready yet and that’s exactly where the work needs to start.
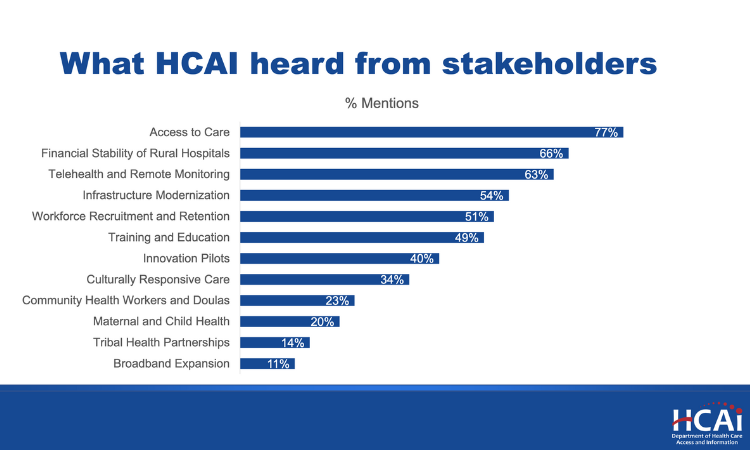
Here is your Rural Health Transformation Program Readiness Checklist.
Let’s get ready together.
1. Have we defined our vision across the five RHTP strategic goals?
CMS frames the RHTP around five strategic goals:
- Make Rural America Healthy Again (prevention and chronic disease)
- Sustainable access
- Workforce development
- Innovative care
- Tech innovation
Before you draft a single paragraph of a proposal, ask:
- What would prevention and chronic disease management look like across our medical, dental, and behavioral health teams? Using integrated products like OroMed could enhance prevention without adding burden
- If we had meaningful new funding, what would “sustainable access” actually look like in our service area? More appointments per day? A stronger dental program? Fewer no-shows? Extended hours?
- What’s our long-term vision for workforce development? Do we want defined career ladders, better onboarding, opportunities for growth, or all of the above?
- What innovative care models do we want to build or scale? School-based care, mobile clinics, embedded dental in medical, integrated behavioral health, a telehealth program?
- How do we want technology to change daily life for our clinicians and patients, not just our IT budget? Think: easier documentation, better decision support, tighter medical-dental integration, more proactive outreach, second-opinion tools.
If you can’t articulate even a rough vision in each of these areas, your rural health transformation program readiness plan will end up being a string of buzzwords instead of a transformation roadmap.
2. Do we have a clear strategy for each of the three “on-the-ground” pillars?
Underneath those four federal goals, health centers will actually execute in three practical pillars:
- Transformative care models
- Technology and tools
- Workforce development and change management
Ask yourself the following:
- Transformative care models:
- Where are the biggest gaps today between what our community needs and what our current model can deliver?
- How will we break down silos between medical and dental health?
- If we want to expand dental access, what does true medical–dental integration look like in our clinics?
- Technology and tools:
- Which tools actually improve access, quality, and provider experience, and which are shiny objects?
- Are we prioritizing clinical second-opinion tools, ambient note-taking, telehealth, and data infrastructure that support real care redesign?
- Workforce and change management:
- Who will champion these changes internally?
- How will we support staff through workflow changes, new tech, and new care models, instead of just “dumping another project” on them?
If your answers are vague, that’s a sign you haven’t made the decisions yet.
3. Do we understand what our state is actually prioritizing?
RHTP is federal, but applications and implementation are state-driven. States submit a Rural Health Transformation Plan to CMS, then design their own program priorities and processes.
Key questions:
- Do we know our state’s approved RHTP plan, its initiatives, and its RFP calendar?
- Which populations, service lines, and geographies is your state emphasizing?
- Are there specific expectations around behavioral health, maternal health, telehealth, or integration?
- Do we know how funds will flow in our state?
- Is our state funding health centers directly, through regional partners, or through contractors?
- Are there regional hub-and-spoke models or consortia being encouraged?
- Are we on our state RHTP office’s update list?
- Have we talked with the state team about where we fit in its initiatives?
- Have we clarified how oral health and dental integration fit into the state’s larger strategy?
If your team is still saying, “We’ll see what the state rolls out and then react,” you’re already behind. Many states are issuing RFPs now, and response windows can be short.
4. Are we fixing access with strategy, not just square footage?
One of RHTP’s core aims is to improve access to care in rural communities, not just keep buildings open.
Before you ask for new space, new chairs, or a new site, ask:
- Have we maxed out access with the space we already have?
- Are scheduling templates optimized? At Optimize Practice Alliance, we’ve used scheduling template redesign to help health centers move from an average 8–13 encounters per provider per day to 50%+ more patient encounters. At Centro Medico, those changes translated into dramatically expanded access with the same number of operatories and staff.
- Are hygiene, restorative, and medical schedules aligned to minimize bottlenecks?
- Do we consistently run on time, or do we lose capacity?
- Do we have a plan to expand access through better systems, not only more bricks and mortar?
- Standardized workflows
- Smarter recall and re-care systems
- Flexible team-based care models
- Can we quantify the access lift of our proposed changes? e.g., “With these changes, we can safely increase dental encounters by X% using existing operatories and staff.”
RHTP reviewers will be looking for transformational leverage, not “more of the same, but more expensive.”
5. What is our recruitment and retention strategy, beyond “we hope people stay?”
RHTP explicitly calls out workforce development and retention as a priority.
So:
- Do we have clearly defined career pathways and levels for clinical and operational roles?
- Can an entry-level team member see a path to becoming a lead, manager, or advanced clinical role?
- How strong is our onboarding and training?
- Can we reliably take a new grad provider from “brand new” to “highly productive and confident” within a defined timeframe?*
- Do we understand why people leave us?
- Are we tracking turnover data and reasons systematically?
- Do we know where burnout is highest and why?
- If we used RHTP dollars for workforce, would it be one-time bonuses, or structural change?**
*Optimize helps health centers build structured clinical development pathways so new-grad providers don’t stay “new” for long. Using a combination of simulation-based training, case review, and progressive skill-building, we’ve supported clinicians in going from fresh graduates to confident, efficient providers who can handle advanced procedures with consistency. This kind of structured development doesn’t just improve clinical performance, it strengthens retention and builds long-term workforce stability.
**If you use RHTP dollars for recruitment or retention incentives, plan for the federal service requirement: anyone in a clinical role who receives an RHTP-funded incentive must work full time in a rural location for five years. CMS can recover funds if the commitment isn’t met. Training pipelines, professional development, career ladders, and leadership development are far more sustainable uses of funds than short-term pay bumps.
If your only workforce lever is bonuses or more money you’re leaving a lot of transformation and long-term stability on the table.
6. Do we actually have an AI strategy, or a list of tools we’re familar with?
RHTP strongly encourages technology-driven, data-driven solutions that support prevention, chronic disease management, and better outcomes.
For most health centers, that should include an intentional approach to AI. Ask:
- Who owns AI strategy in our organization?
- Do we have an AI governance group or at least a designated champion?
- Do we know what we’re comfortable with and what we’re not?
- Are we piloting tools that actually free up clinical time and improve quality?
- Ambient note-taking to give clinicians time back
- Clinical second-opinion tools (e.g., radiograph analysis, risk scoring, lab decision support)
- Predictive outreach to identify high-risk patients earlier
- How will we evaluate AI tools?
- Impact on access, quality, provider experience, and equity
- Data privacy and security
- Alignment with our state’s RHTP priorities
RHTP is a rare chance to build a responsible AI foundation instead of reacting piecemeal to vendor pitches. Optimize Practice Alliance is leading the charge when it comes to AI in dental care. Our AI rollouts routinely give dentists back 26 minutes a day by wiping out the bulk of their documentation burden. And because our CEO, Josh Gwinn, is the founding president of the Denver chapter of AAIA Global, we’re not guessing at where AI is going, we’re helping shape the standards for safe, effective clinical use.
7. How ready are we for change management, not just project management?
Most failed organization transformations don’t die because the idea was bad. They die because nobody planned for the human side.
Ask:
- Who is our internal change leader for RHTP?
- Is there a cross-functional group (medical, dental, behavioral health, operations, finance, IT) that meets regularly?
- How will we communicate changes to staff and patients?
- Do we have a plan for training, feedback loops, and iterating without burning people out?
- What will success look like in year 1, year 3, and year 5?
- Are we setting realistic milestones, or just “Everything will be transformed by 2030”?
If your RHTP plan doesn’t have a change-management backbone, the best strategy in the world will stall in the day-to-day.
8. Can we show sustainability once the grant dollars sunset?
States and CMS will be looking hard at whether proposed projects will survive beyond the funding window.
Your team should be able to answer:
- What happens when RHTP funding ends? Does the project collapse, or does it become self-sustaining through improved revenue, cost savings, or other funding streams?
- Do we have a financial model that ties clinical transformation to financial stability? For example: more completed treatment plans, higher kept-appointment rates, improved coding and documentation, reduced avoidable ED visits.
- Are we avoiding uses of funds that can’t be maintained? e.g., staffing models that only work if grant dollars are permanent.
If you can’t show a credible path to sustainability, you’re not fully prepared, no matter how strong your narrative is.
9. Where are we already strong and who are the right partners for the rest?
Finally, a simple but important set of questions:
- What do we already do well that RHTP can help us scale? Maybe it’s a small but successful mobile-based dental program, or an integrated medical-dental workflow in one clinic.
- Where do we openly need outside expertise, practice operations and scheduling redesign? Our Practice Optimization Process™ is a strategic, proven framework with a track record of transforming underperforming clinics into high-efficiency, high-access care teams. It’s the same system we’ve used to redesign workflows, tighten scheduling templates, and unlock dramatic gains in patient encounters, without adding staff or operatories.
- Do we have a plan for dental and medical-dental integration? Optimize helps health centers stand up fully integrated medical–dental care models that bring preventive dental evaluations directly into primary care: no extra chairs, no added complexity. This integrated approach consistently uncovers hidden oral-health needs, drives earlier intervention, and opens entirely new access points inside the existing footprint. It’s one of the fastest, most sustainable ways to expand care without expanding your building.
- What are our AI governance and clinical second-opinion tools?
- What workforce pathways and training can we offer?
- Who are we going to call in before we write the proposal? Implementation partners should be at the design table, not just in the budget appendix.
Optimize Practice Alliance works with community health centers across the country on exactly these questions, from building sustainable dental programs and integrated care models to designing AI-enabled, clinician-friendly workflows. RHTP is new, but the fundamentals of transformation are not.
If reading this raised more questions than answers, that’s a good sign. It means you’re thinking at the right level. Here’s a simple next step:
Pull this list of questions into your next leadership meeting. Have your team rate each area (Sustainable Access, Workforce, Innovative Care, Tech & AI, Change Management, Sustainability) as:
- We’re clear and ready
- We’ve started, but it’s shaky
- We haven’t really tackled this yet
Rural Health Transformation Program Readiness
Ready to move from awareness to readiness?
Our Rural Health Transformation Program Readiness Guide was created to help leaders translate RHTP expectations into operational clarity, so your organization is positioned not just to access funding, but to execute meaningful, sustainable transformation.
The question to ask: “Are our systems, operations, and leadership aligned to deliver on what the RHTP requires?”
Download the RHTP Guide for Health Center Executives to pressure-test your readiness, identify where optimization will matter most, and ensure your health center is prepared for what’s ahead, before the next bend in the road.